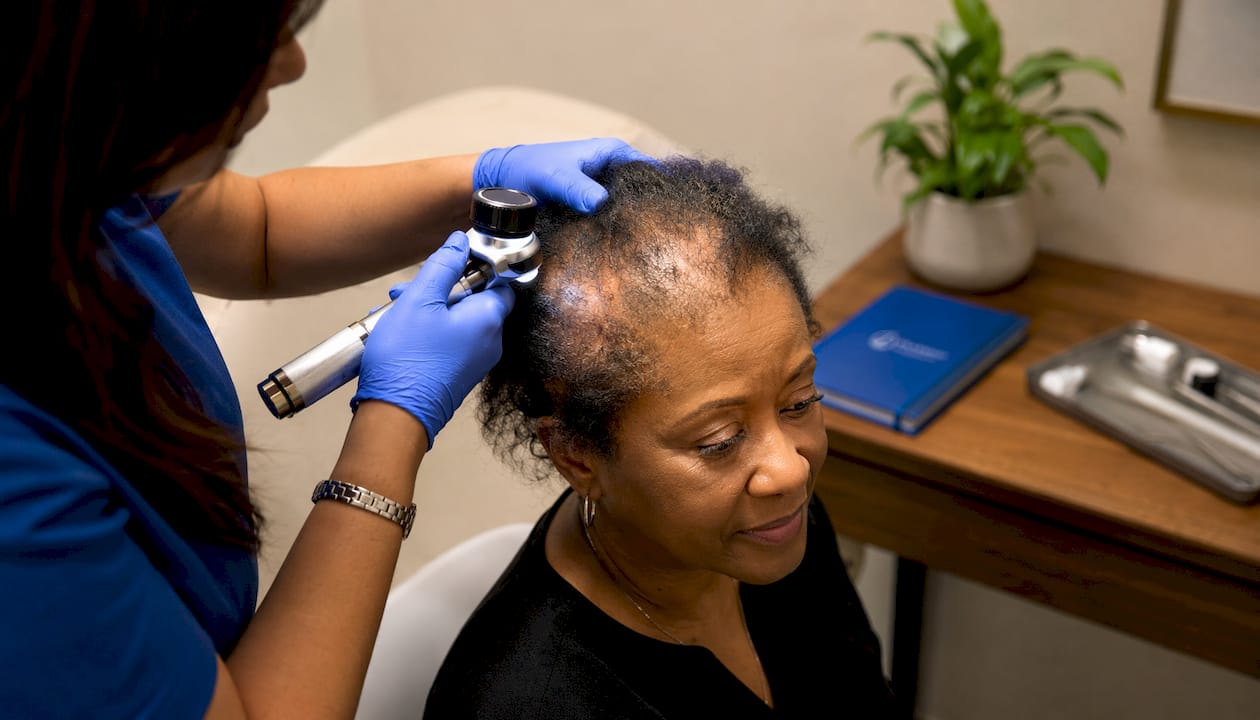Scarring alopecia explained: a UK patient guide
What is scarring alopecia, and how does it differ from other hair loss?
Scarring alopecia, also known as cicatricial alopecia, is a group of disorders in which hair follicles are irreversibly destroyed
and replaced by scar tissue, resulting in permanent hair loss. Unlike non-scarring alopecia, where the follicle remains structurally intact and regrowth is possible, scarring alopecia closes off any prospect of natural recovery in the affected area. That distinction is clinically critical and shapes every decision that follows.
The condition is divided into two broad classes. Primary scarring alopecia targets the follicle directly, with inflammation attacking the epithelial stem cells in the hair follicle bulge. Secondary scarring alopecia arises when follicle destruction is a consequence of another process altogether, such as burns, radiation, or severe infection. Within the primary class, subtypes are grouped by the dominant inflammatory cell type: lymphocytic, neutrophilic, or mixed. The two most common forms are lichen planopilaris (LPP) and frontal fibrosing alopecia (FFA), both of which predominantly affect women.
- Follicle destruction is permanent; lost follicles cannot be regenerated by any current treatment.
- Primary cicatricial alopecia is classified as lymphocytic, neutrophilic, or mixed.
- LPP and FFA are the most prevalent types in the UK.
- Non-scarring alopecia (e.g., alopecia areata, telogen effluvium) leaves follicles intact and carries potential for regrowth.
- The Primary Care Dermatology Society (PCDS) classifies scarring alopecia as irreversible, making early referral a priority.
Table of Contents
How is scarring alopecia diagnosed in the UK?
Distinguishing scarring from non-scarring alopecia is the single most important step in clinical assessment, because the management pathway diverges entirely at that point. A clinician examining the scalp will look for the loss of follicular ostia (the small openings through which hairs emerge), a shiny or atrophic surface, and any perifollicular inflammation or pigmentary change. These signs point strongly toward a scarring process.
Dermoscopy has become an indispensable tool at this stage. It can reveal the absence of follicular openings, atrophic skin, and tufting patterns such as “dolls hair” tufting, where multiple hairs emerge from a single follicular unit as surrounding follicles are destroyed. Dermoscopic findings guide the urgency of onward referral and help clinicians at EIV Diagnostics and similar dermatopathology services
prepare for targeted biopsy analysis.
A scalp biopsy remains the gold standard for confirming the diagnosis and identifying the specific subtype. Patients with suspected scarring alopecia in the UK require urgent dermatology referral to minimise further permanent loss. In primary care, a blood screen is typically arranged before that referral.
Diagnostic steps summarised:
- Clinical examination for loss of follicular ostia, shiny or atrophic scalp, and perifollicular inflammation.
- Dermoscopy to detect tufting, absent follicular openings, and skin texture changes.
- Scalp biopsy for definitive subtype confirmation.
- Blood tests in primary care: FBC, U&E, LFT, ferritin, TFT, and ANA.
- Urgent dermatology referral once scarring alopecia is suspected.
What symptoms should you look out for?
Symptoms of scarring alopecia vary considerably between patients and between subtypes. Some people experience significant discomfort; others notice nothing beyond progressive hair loss. That variability makes the condition easy to underestimate.
- Itching, burning, pain, or altered sensation on the scalp.
- Patchy or diffuse hair loss, often with a shiny, smooth surface where hair has been lost.
- Perifollicular scaling or redness in active phases.
- Tufting of hairs in affected areas.
Crucially, inflammation may be entirely subclinical, meaning the disease can be actively destroying follicles beneath the skin surface with no visible redness or swelling. Patients who feel no symptoms should not assume their condition is stable. FFA, for example, is asymptomatic in the majority of cases, with only around a quarter of patients reporting itching or pain in the affected hairline area. Regular clinical monitoring is the only reliable way to assess activity.
What treatment options are available for scarring alopecia in the UK?
The goal of treatment is unambiguous: stop further follicle destruction. No current therapy can restore follicles that have already been lost. Early intervention therefore carries far more weight than it does in non-scarring conditions, where a delayed start still leaves regrowth possible.
Medical management draws on several drug classes, each targeting the inflammatory process through a different mechanism:
- Topical and intralesional corticosteroids:
First-line agents applied directly to active areas to suppress localised inflammation.
- Calcineurin inhibitors
(e.g., tacrolimus): Used where steroids are not tolerated or as adjuncts.
- Tetracycline antibiotics
(e.g., doxycycline): Prescribed for their anti-inflammatory properties
rather than antimicrobial action, typically for six months before response is assessed.
- Oral hydroxychloroquine:
Commonly used in lymphocytic subtypes such as LPP and FFA; trialled over 4–6 months with monitoring including annual eye examinations for retinal toxicity.
- Immunosuppressants
(e.g., ciclosporin, methotrexate): Reserved for refractory cases; require close monitoring with regular blood tests.
For patients exploring hair loss medication options
alongside specialist care, understanding which drug class applies to their specific subtype is an important first conversation with their dermatologist.
How should you manage scarring alopecia over the long term?
Scarring alopecia is a chronic condition. Achieving disease stability is not a one-time event; it requires sustained monitoring and, for many patients, ongoing treatment adjustments over years. Patients should expect regular clinic visits, periodic blood tests, and surveillance for medication side effects.
Hydroxychloroquine in particular carries a risk of retinal toxicity with long-term use, making annual eye examinations non-negotiable. Immunosuppressants require blood monitoring to detect hepatic or haematological changes before they become clinically significant.
Beyond pharmacological management, the psychosocial burden of permanent hair loss is real and should be addressed directly. Referral to psychological support services or counselling is appropriate for many patients. Optimising diet, maintaining micronutrients within reference range, and adopting a gentle scalp care routine all contribute to the overall management plan. Organisations such as Alopecia UK provide peer support and guidance on cosmetic camouflage options that can be just as meaningful as active treatment for day-to-day wellbeing.
Long-term monitoring checklist:
- Regular dermatology follow-up to assess disease activity.
- Annual eye examinations for patients on hydroxychloroquine.
- Periodic blood tests for patients on immunosuppressants.
- Psychological support referral where appropriate.
- Dietary optimisation, aiming for micronutrients at mid-reference range or above.
What hair restoration options are available once the condition is stable?
Hair restoration after scarring alopecia is possible, but the timing and approach require careful clinical judgement. Hair transplant surgery is generally deferred until the inflammatory process has been well-controlled for an extended period, typically several years. Proceeding during active disease carries a high risk of graft failure and potential exacerbation of the underlying condition.
When disease inactivity is confirmed, surgical restoration becomes a realistic option for suitable patients. The procedure involves transplanting follicular units from a healthy donor area into the scarred region, a technically demanding process given the altered tissue environment. Patients with conditions such as CCCA should also be aware of an elevated risk of keloid scar formation.
While awaiting surgical eligibility, or for those who prefer non-surgical routes, several options provide meaningful cosmetic benefit:
- Scalp micropigmentation (SMP):
A non-surgical technique that replicates the appearance of hair follicles using specialised pigment, creating the look of a closely cropped scalp.
- Wigs and hairpieces:
High-quality options that can be prescribed through NHS dermatology services in cases of significant psychological distress.
- Cosmetic camouflage products:
Fibres, sprays, and concealers that reduce the visual contrast between hair and scalp.
Glasgowhairtransplantclinics offers a full range of hair restoration services across the UK, with GMC-registered surgeons and CQC-registered clinics. Whether you are exploring hairline transplant options
or scalp micropigmentation, the team provides personalised consultations to assess your suitability and set realistic expectations. A free online or face-to-face consultation is available to help you understand your options before committing to any procedure.
Pro Tip:
If you have been diagnosed with a scarring alopecia subtype, ask your dermatologist for a written record of disease activity at each visit. This documentation becomes essential when assessing surgical eligibility later.
Key takeaways
Scarring alopecia requires early diagnosis and sustained treatment to halt follicle destruction, as lost follicles cannot be restored by any current medical or surgical intervention.
| Point |
Details |
| Permanent follicle loss |
Destroyed follicles cannot regenerate; the treatment goal is to stop further loss, not reverse it. |
| Urgent referral matters |
UK patients with suspected scarring alopecia need urgent dermatology referral to minimise irreversible damage. |
| Subclinical inflammation |
Absence of visible redness does not confirm disease inactivity; monitoring remains necessary. |
| Treatment timelines |
Hydroxychloroquine is trialled over 4–6 months; tetracycline antibiotics are typically assessed after six months. |
| Surgery requires stability |
Hair transplant surgery is deferred until inflammation has been inactive for several years to reduce graft failure risk. |
FAQ
What is the difference between scarring and non-scarring alopecia?
Scarring alopecia permanently destroys hair follicles and replaces them with scar tissue, making hair loss irreversible. Non-scarring alopecia leaves follicles intact, so regrowth remains possible with appropriate treatment.
Can scarring alopecia be cured?
There is currently no cure for scarring alopecia. Treatment focuses on halting disease progression and preserving remaining hair through anti-inflammatory therapies.
How is scarring alopecia diagnosed?
Diagnosis involves clinical examination, dermoscopy to detect absent follicular openings and tufting patterns, a scalp biopsy for subtype confirmation, and blood tests including FBC, ferritin, TFT, and ANA.
Is a hair transplant possible if you have scarring alopecia?
A hair transplant may be considered once the inflammatory process has been well-controlled for several years, but it carries a higher risk of failure than standard transplantation and requires thorough specialist assessment beforehand.
What types of scarring alopecia are most common in the UK?
Lichen planopilaris (LPP) and frontal fibrosing alopecia (FFA) are the two most prevalent types, both classified as lymphocytic primary cicatricial alopecias and most commonly affecting women.
Recommended
What scarring alopecia means
Scarring alopecia describes hair loss in which follicles are damaged and replaced by scar tissue. Hair cannot regrow from a follicle that has been destroyed. Treatment aims to control the cause and protect the remaining hair.
Several conditions can cause it, including lichen planopilaris and frontal fibrosing alopecia. Scarring can also follow an injury, burn or infection. A receding hairline or bald patch alone cannot establish the diagnosis.
Signs worth getting checked
Changes can include patchy hair loss, a smooth or shiny scalp, scaling around hairs, itching, burning or tenderness. Symptoms vary, and a lack of discomfort does not establish that the condition is inactive. Seek medical assessment promptly if hair loss is progressing or the scalp is inflamed.
How it is assessed
A clinician examines the scalp and asks about the pattern and timing of hair loss, symptoms, medicines and relevant medical history. A dermatologist may use magnification and recommend a scalp biopsy to clarify the diagnosis. Blood tests depend on the suspected cause; everyone does not need the same set of investigations.
Treatment depends on the diagnosis
For lichen planopilaris, options can include steroid preparations or injections and, in selected cases, oral medicines such as hydroxychloroquine or immunosuppressants. Response varies. Each medicine has its own risks and monitoring requirements, which the prescriber should explain. The British Association of Dermatologists’ lichen planopilaris leaflet
explains these options and their limitations.
Do not start or stop a prescribed treatment on the basis of a general article. Ask how disease activity will be assessed, when your treatment will be reviewed and which symptoms or side effects should prompt contact with the dermatology team.
Can a hair transplant help?
A transplant does not treat the underlying inflammatory condition. Surgery may be considered for some people once the condition has been stable for an extended period, but recurrence can affect transplanted hair. A decision needs an assessment of the diagnosis, disease activity, donor hair and recipient skin. See the BAD guidance on restoration after lichen planopilaris.
There is no single waiting period that makes surgery suitable for everyone. Bring your dermatology reports and treatment history to any surgical consultation, and ask whether further specialist input is needed before planning a procedure.
Living with permanent hair loss
Wigs, hairpieces or cosmetic camouflage may help with appearance without surgery. Discuss scalp sensitivity when choosing products. If hair loss is affecting your confidence or daily life, tell your GP or dermatology team so that support can be considered alongside treatment.
Discussing restoration in Birmingham
For an enquiry about hair restoration at Edmund House, 12–22 Newhall Street, Birmingham B3 3AS, contact the Birmingham clinic. Include any existing diagnosis and whether you are under dermatology care. A restoration enquiry does not replace assessment or treatment of active scalp disease.